
Making sense of fall vaccine guidance for the immunocompromised
September 16, 2026

The more you understand about primary immunodeficiency (PI), the better you can manage it. Learn about PI diagnoses and treatment options.

Living with primary immunodeficiency (PI) can be challenging, but you’re not alone—many people with PI lead full and active lives. With the right support and resources, you can, too.

Be a hero for those with PI. Change lives by promoting primary immunodeficiency (PI) awareness and taking action in your community through advocacy, donating, volunteering, or fundraising.

Whether you’re a clinician, researcher, or an individual with primary immunodeficiency (PI), these resources will help you advance the field. Get details on surveys, grants, and clinical trials.
This year, professional medical organizations are stepping up to provide recommendations going into cold and flu season. The Infectious Disease Society of America’s (IDSA) guidelines for people who are immunocompromised are the most relevant for people with primary immunodeficiency (PI), but other organizations have published guidelines as well:
COVID-19, influenza (the flu), and respiratory syncytial virus (RSV) can all be serious, life-threatening illnesses in people with PI. Getting vaccinated and making sure everyone in your household is vaccinated is one of the best ways to protect yourself from these germs. Your healthcare provider may also recommend monoclonal antibodies, depending on your situation.
Because SARS-CoV-2 and influenza strains shift from year to year, it’s important to get seasonal COVID and flu shots every year. While immunoglobulin (Ig) replacement therapy protects against many diseases, it takes months to manufacture and generally does not have enough antibodies against the latest virus strains to protect you well. That’s why the foundation’s Medical Advisory Committee (MAC) continues to recommend that everyone with PI, whether you’re on Ig or not, get these seasonal vaccines.
Respiratory syncytial virus (RSV) is different. Only people who have not been vaccinated against RSV before need to get immunized.
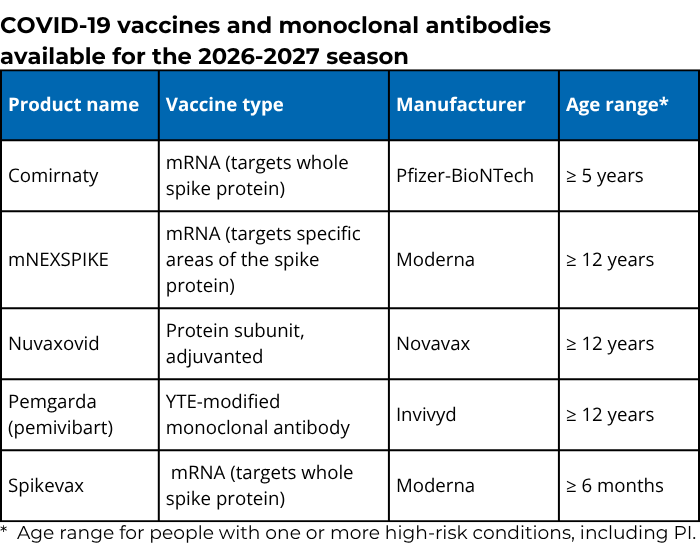
COVID-19 has now settled into a pattern of two peaks a year: one starting in August and another in January. Updated 2026-2027 COVID-19 vaccines are arriving just as the late summer peak hits. They target one strain of the SARS-CoV-2 virus, the XFG subvariant.
Here’s what to know:
There are four Food and Drug Administration (FDA)-approved COVID vaccines available, as well as one FDA-authorized monoclonal antibody. None of the vaccines are live, so they are all safe for people with PI and their loved ones.
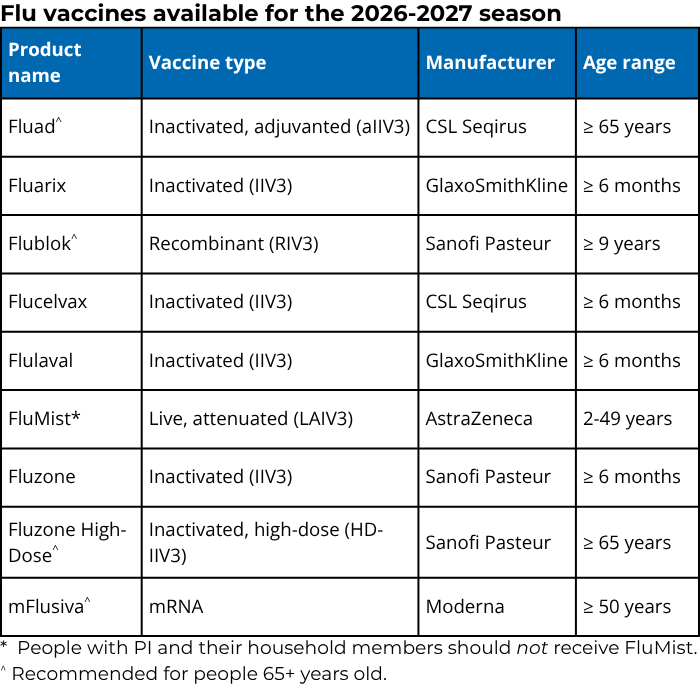
For 2026-2027, flu vaccines protect against two influenza A and one influenza B strains. Importantly, all three strains are new this year.
Here’s what to know:
There are nine Food and Drug Administration (FDA)-approved flu vaccines available. Only FluMist is a live vaccine.
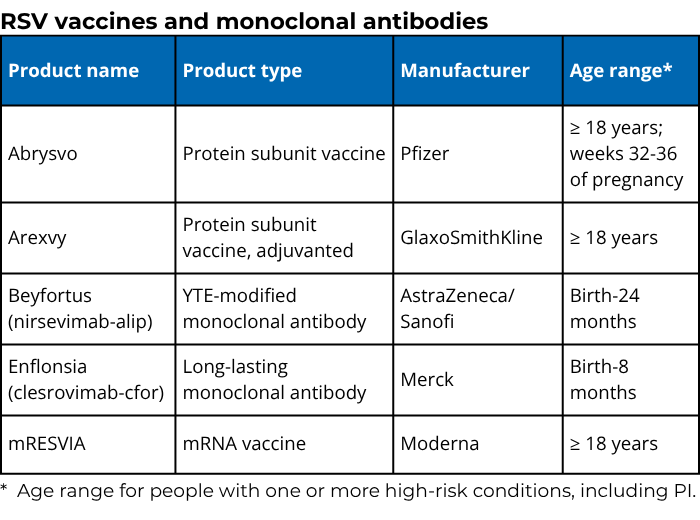
Unlike COVID and the flu, you don’t need to get vaccinated for RSV more than once in your lifetime. However, IDSA recently expanded its recommendations on who should get vaccinated.
Here’s what to know:
Three RSV vaccines and two monoclonal antibodies are currently approved. None of the vaccines contain live virus, so they are all safe for people with PI and their loved ones.
IDSA’s guidelines specifically address timing of vaccines for PI and other categories of immunocompromise. Since the COVID, flu, and RSV vaccines recommended for people with PI are not live vaccines, there is no need to time vaccination around intravenous (IVIG) or subcutaneous (SCIG) Ig infusions. However, there are other situations where timing is important, including:
The guidelines point out that it is safe to get all the fall vaccines you need at the same time. However, each vaccine should be given at a site that is at least one inch away from any other site. Being able to get all your vaccines during one appointment simplifies planning, especially if you’re timing vaccines around other medical considerations.
Also, remember that vaccines are a crucial tool during respiratory virus season, but you should take advantage of other tools, too. Masking in public places, avoiding sick people, and good hand and surface hygiene can cut down on your exposure to all germs, not just the big ‘cold and flu season’ threats.
Finally, make sure you’re prepared in case you do get COVID, the flu, or RSV. How will you get tested? What antivirals does your healthcare provider recommend that you take (or avoid) and how will you get them? What symptoms should you pay the most attention to?

This page contains general medical and/or legal information that cannot be applied safely to any individual case. Medical and/or legal knowledge and practice can change rapidly. Therefore, this page should not be used as a substitute for professional medical and/or legal advice. Additionally, links to other resources and websites are shared for informational purposes only and should not be considered an endorsement by the Immune Deficiency Foundation.



Receive news and helpful resources to your cell phone or inbox. You can change or cancel your subscription at any time.




